




Unsafe Abortion: More Information Needed for True Informed Consent

The Maryland Office of Health Care Quality is investigating the tragic death of 29-year-old Jennifer Morbelli, who died after a suspected late-term abortion procedure performed at a controversial abortion clinic in Germantown, Maryland. They are right to do so. However, a more comprehensive response is warranted from the wider obstetrical and medical community. Americans should be outraged by the paucity of evidence-based information regarding abortion procedures and complications in the United States.
Complications from medical and surgical procedures are a reality of medical intervention. No matter how healthy a patient or how low-risk a procedure, adverse and sometimes tragic unforeseeable outcomes can occur. The death of a single patient, though tragic, does not by itself invalidate a particular medical treatment or surgical procedure. (Conversely, of course, the relative safety of a procedure does not determine its ethical character.) However, the medical profession strives to mitigate adverse outcomes and provide best care to patients by embracing evidence-based medical and surgical practices, rigorously tested and shown to produce greater benefit than harm to patients. Because medical and surgical interventions involve some patient risk, patients must be apprised of such risks through the process of informed consent, ideally allowing patients to weigh benefits and risks for themselves.
The case of abortion procedure research is, however, woefully inadequate. In the aftermath of an abortion patient’s unexpected death, some point to the involved procedure as “unsafe,” while others claim the same procedure to be necessarily beneficial. The fact remains that in the United States neither side can argue from reliable, evidence-based abortion data. Such glaring omission in the science of obstetrics is a gross disservice to patients. As recently detailed by obstetrician-gynecologist John Thorp, Jr., the U.S., unlike other countries, does not have a systematic method of tracking abortion procedures or complications. U.S. abortion research is plagued by the lack of a national registry and reliance on largely survey methodology. Thus the true incidence, safety, and short- and long-term health effects of abortion procedures are imprecisely known in the United States.
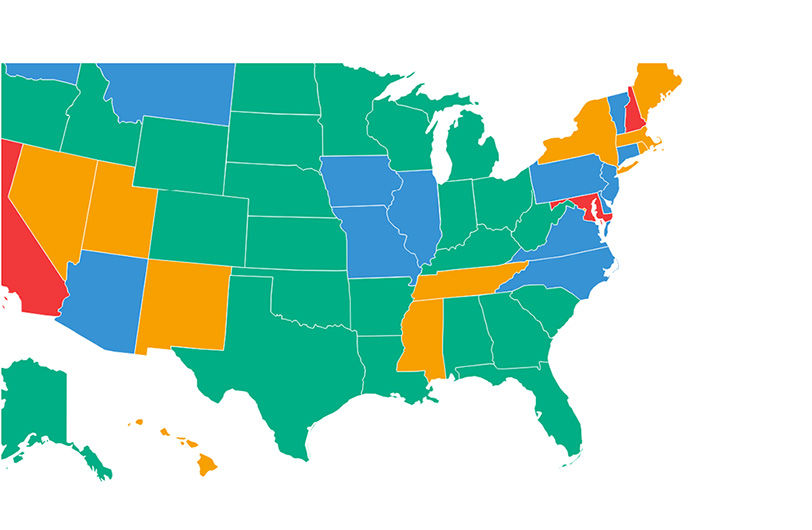
While 47 states require abortion providers to report minimal abortion statistics to state authorities, only 27 states require reporting of post-abortion complications. National data is inadequate and incomplete due to wide variability in state reporting requirements and due to the fact that state reporting to the federal Centers for Disease Control (CDC) is entirely voluntary. For instance, the state of California has not submitted abortion data to the CDC in the past decade. Inaccurate information is readily apparent, if infrequently acknowledged. In one year, comparing CDC Abortion Surveillance documents to popular press reports showed the omission of four post-abortion deaths from state statistics. The fact that we may be omitting risk information to abortion-seeking patients due to inadequate data collection and analysis is also suggested by the fact that countries with mandatory reporting show increased abortion-related mortality rates above U.S. estimates.
It is worth noting that a national registry of abortion data is not primarily a regulatory tool, but a scientific one. Mandatory reporting to national procedure registries is a research method used by numerous surgical specialties to collect comprehensive, precise information on surgeries and other procedures that cannot be ethically studied by means of standard patient randomization – that is, assigning different procedures to different women on a random basis – as is the case with abortion procedures. These centralized databases allow for standardized data collection based on consistent criteria. Patient anonymity is preserved through the non-identifying nature of the collected data, while at the same time a large body of reliable information is available for widespread study. Analysis of such information by researchers in turn provides an evidence-based understanding of the risks and benefits of the surgical interventions, enabling medical practice to change accordingly for the greater health and safety of patients.
In a statement to the press referencing the death of Jennifer Morbelli, NARAL Pro-Choice Maryland emphasized that their concern is “first and foremost for the safety and health of women.” It seems reasonable, then, that the death of Jennifer Morbelli offers one area of common ground for both pro-life and pro-choice communities. Americans, and the medical community, should advocate for national abortion data-gathering mechanisms that adequately support evidence-based information on the short- and long-term consequences of abortion procedures. Without such information, the medical community does a potentially grave disservice to women seeking pregnancy termination, and true informed consent cannot be provided.
Elizabeth Ann M. Johnson, M.D. is a Fellow, Program for Human Rights and Health, University of Minnesota School of Public Health.